

Friday, 11 September, 2026
Most men who search this have already tried the obvious thing. They lost weight. The stomach went, the face changed, the arms got leaner — and the chest stayed almost exactly as it was.
That experience is the clearest clue you can have, and it points to a specific answer. Because there are two entirely different conditions behind what men variously call gyno, man boobs or moobs, and only one of them responds to anything you do in a gym.
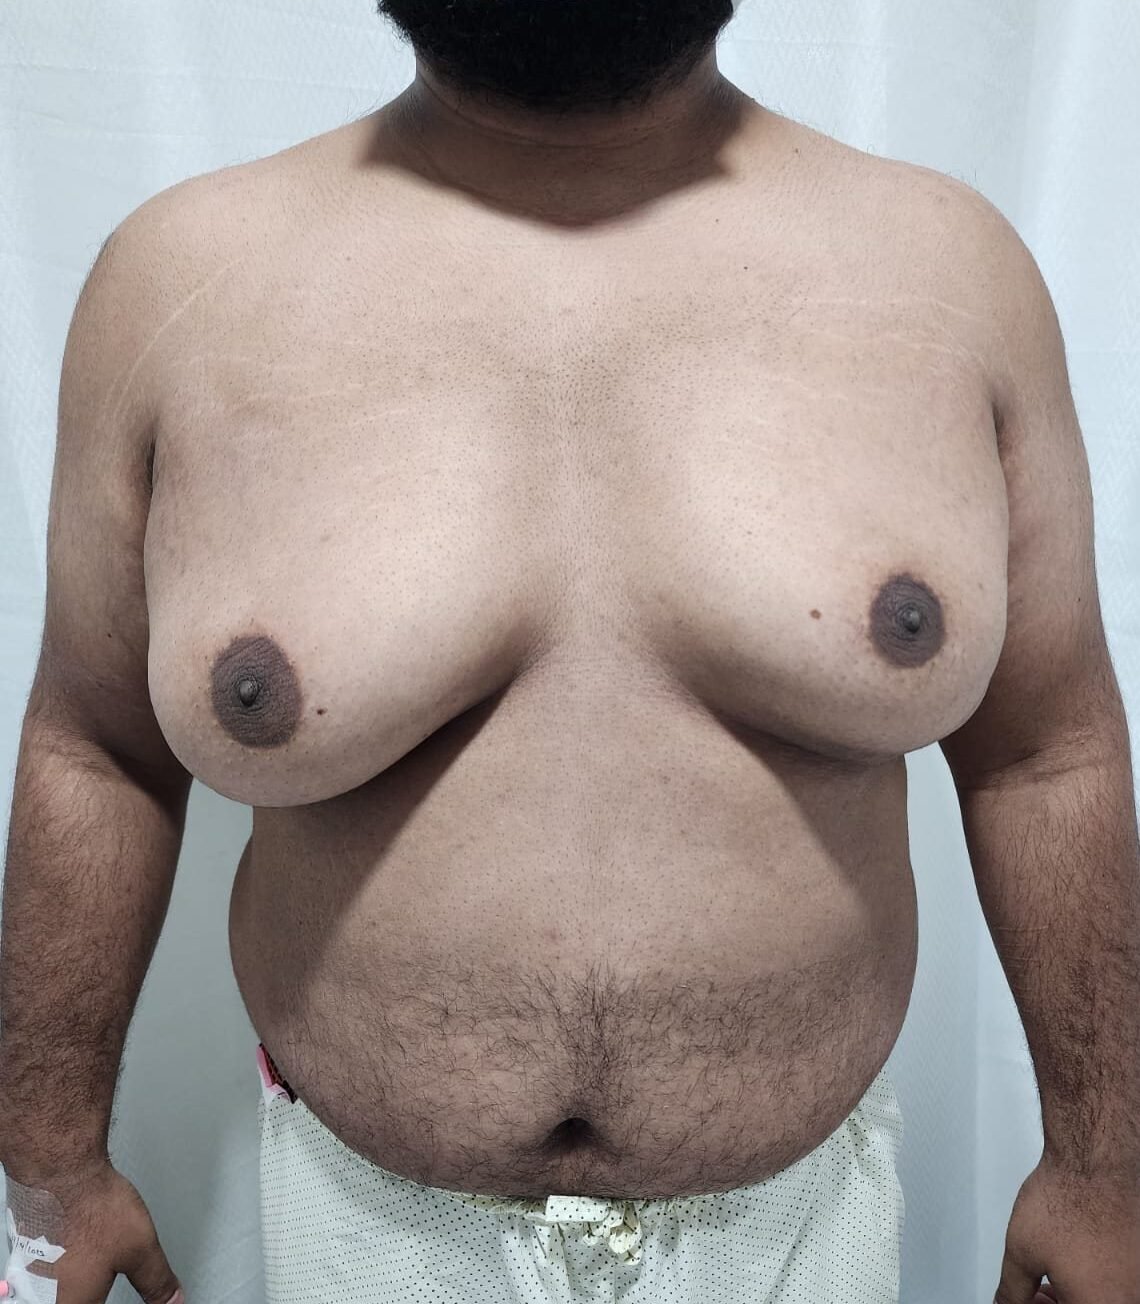
True gynecomastia is enlargement of the glandular breast tissue in men — actual breast gland, proliferating in response to a shift in the balance between oestrogen and testosterone activity.
Pseudogynecomastia, sometimes called lipomastia, is increased fat in the chest with no enlargement of glandular tissue at all.
Same silhouette in a fitted t-shirt. Completely different tissue underneath. And because they are different tissue, they respond to completely different things — fat to a calorie deficit, gland to neither diet nor exercise.
A third possibility, and probably the most common one in practice, is that you have both.
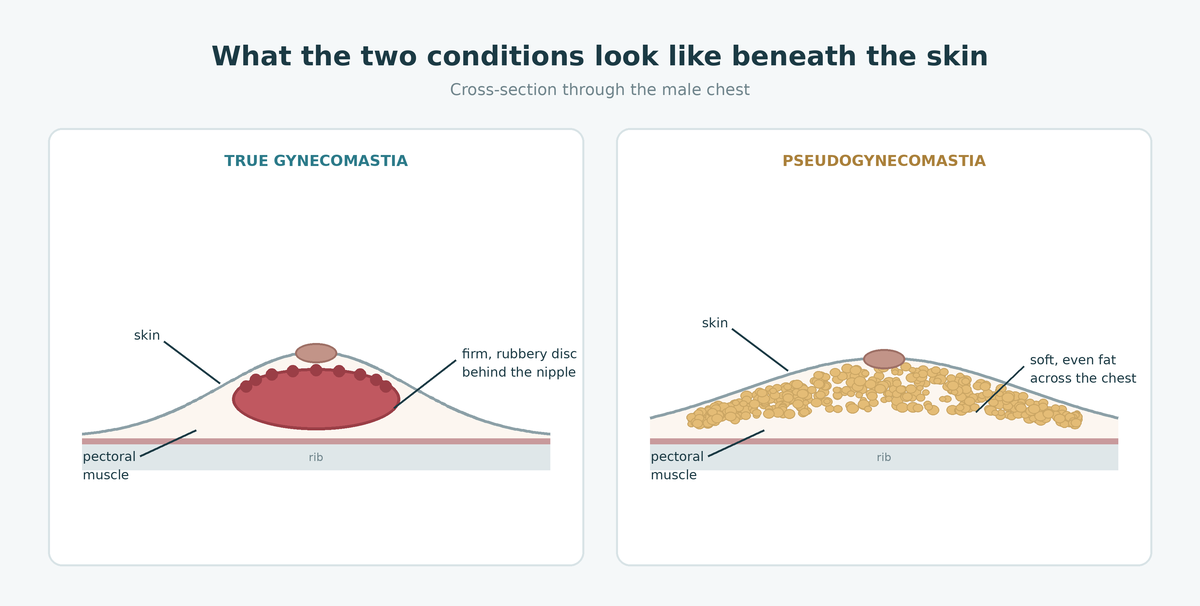
There is a standard clinical examination for this, and you can do a rough version of it yourself.
Lie flat on your back. This matters more than it sounds — lying down lets chest fat spread and fall to the sides, which makes anything firmer stand out. Standing up, fat and gland blur together.
Now bring your thumb and forefinger together from opposite sides of the nipple, moving slowly inward until they meet.
If they meet without hitting anything — no resistance, just soft, uniform, doughy tissue all the way in — that pattern is consistent with fat.
If you feel a distinct rim or disc of firmer, rubbery tissue encircling the nipple, roughly symmetrical all the way around, and noticeably different in consistency from the softer tissue further out, that pattern is consistent with glandular tissue.
A few additional signals worth noticing:
Published sources differ on how large the disc needs to be before it counts — some describe a rim greater than half a centimetre, others use a threshold closer to two centimetres. Don’t get stuck on measuring it. What clinicians actually weigh is the character of the tissue, not the millimetres.
And to state the obvious: this is something to notice, not something to diagnose. A self-check tells you whether to book an appointment. It does not tell you what the tissue is.
If your problem is purely pseudogynecomastia, weight loss is genuinely the answer — the American Academy of Family Physicians states directly that patients can be reassured that weight loss will resolve it.
But excess body fat doesn’t only mimic gynecomastia. It can help cause it. Fat tissue contains an enzyme complex called aromatase, which converts testosterone into oestradiol. More body fat means more aromatase activity, which shifts the oestrogen-to-testosterone balance in the direction that stimulates glandular growth. One review reports that men with a BMI of 25 or above have a substantially higher likelihood of gynecomastia or pseudogynecomastia.
So carrying extra weight can produce chest fat and real glandular tissue at the same time — which is exactly why so many men lose weight, watch the rest of their body change, and find a firm disc still sitting behind the nipple.
Losing weight is still worth doing, and not only for the fat. Research shows that as men lose weight, total testosterone rises and oestradiol falls — the hormonal environment moves in a favourable direction.
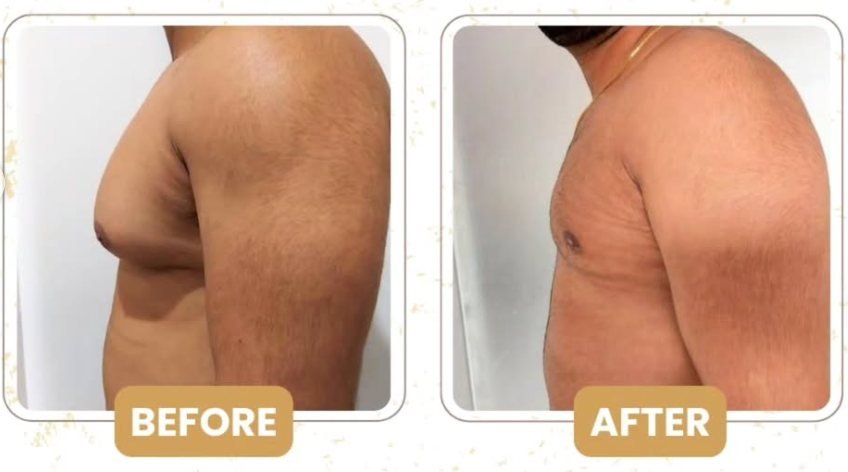
For a large group of men, “lose weight” was never useful advice in the first place.
Lean men, competitive athletes and bodybuilders turn up with gynecomastia regularly, often with body fat low enough that there is simply no fat left to lose. In this group the chest can actually look worse as they get leaner, because the surrounding fat that was blurring the outline disappears and leaves the glandular disc standing proud of a flat, defined chest. Building the pectoral muscle underneath pushes it forward further still.
If you are training hard, eating carefully, visibly lean everywhere else, and the chest has not changed — that is not a discipline problem. It is a tissue problem, and it is one of the clearest presentations of true gynecomastia there is.
Anabolic steroids deserve particular attention here. The mechanism is often misunderstood. Exogenous androgens are converted to oestradiol through the same aromatase pathway described above. Taking testosterone or a related compound can therefore raise oestrogen activity at the breast — which is why gynecomastia is a recognised consequence of anabolic steroid use rather than a paradox.
Two practical points follow. Tissue that develops during a cycle does not reliably disappear when the cycle stops, particularly once it has been present for several months and become fibrous. And surgery performed while steroid use continues is working against an ongoing cause.
If this applies to you, say so at your consultation. It changes the assessment, it is more common than most men assume, and no competent surgeon is going to be shocked.
The underlying mechanism is always the same: a shift in the ratio of oestrogen to androgen activity at the breast — not necessarily an abnormal level of either hormone in isolation.
The causes behind that shift, with approximate frequencies reported in adults:
| Cause | Roughly |
|---|---|
| Physiological, including persistent pubertal gynecomastia | 25% |
| Idiopathic — no cause identified | 25% |
| Medications and substances | 10–25% |
| Cirrhosis or liver disease | 8% |
| Primary hypogonadism | 8% |
| Tumours | 3% |
| Hyperthyroidism, secondary hypogonadism, kidney disease | ~5% combined |
Two things stand out. Roughly half of adult cases are either normal physiology or have no identifiable cause. And medication is the most common identifiable external cause — the one most often missed.
Drug classes commonly implicated include anti-androgens such as spironolactone and finasteride, anabolic steroids, some antiretrovirals, certain antidepressants and anti-anxiety medicines, some antibiotics, opioids, ulcer medications, chemotherapy agents and some heart medicines. Spironolactone in particular is reported to cause gynecomastia in up to 10% of users.
Alcohol, marijuana and some recreational drugs are also implicated, as are underlying conditions including liver disease, kidney failure, thyroid disorders and, less commonly, tumours of the testes, adrenal glands or pituitary.
If you developed gynecomastia within months of starting a new medication, that is worth raising with the doctor who prescribed it — before you consider anything surgical.
Gynecomastia during puberty is normal and common. Published figures suggest somewhere between half and 60% of adolescent boys develop some degree of it, typically peaking around ages 13 to 14.
The large majority resolves without any treatment. Sources vary on exactly how long — commonly quoted ranges run from six months to two years, with most cases settling within about three years. A minority, estimated in the region of 10–20%, still have some breast tissue by the late teens or early twenties.
Two different questions get tangled together here, so it is worth separating them.
Assessment can happen at any time, at any age. There is no reason to wait before having the chest examined, the cause identified, medications reviewed and blood tests done if they are indicated. If anything, early assessment is more useful, because drug treatment — where it is appropriate at all — works best in the first several months, before the tissue becomes fibrous.
Surgery is a separate decision, and the timing depends on who you are. In adults there is no waiting period; once gynecomastia is established and long-standing, delaying achieves nothing. In adolescents, surgery is normally postponed until puberty is complete, because operating before that finishes carries a clearly documented risk that the tissue simply grows back. Waiting is not a delay tactic — it is what prevents a second operation.
Deferring surgery is not the same as doing nothing. The assessment, the reassurance and the exclusion of an underlying cause should all happen at the first visit.
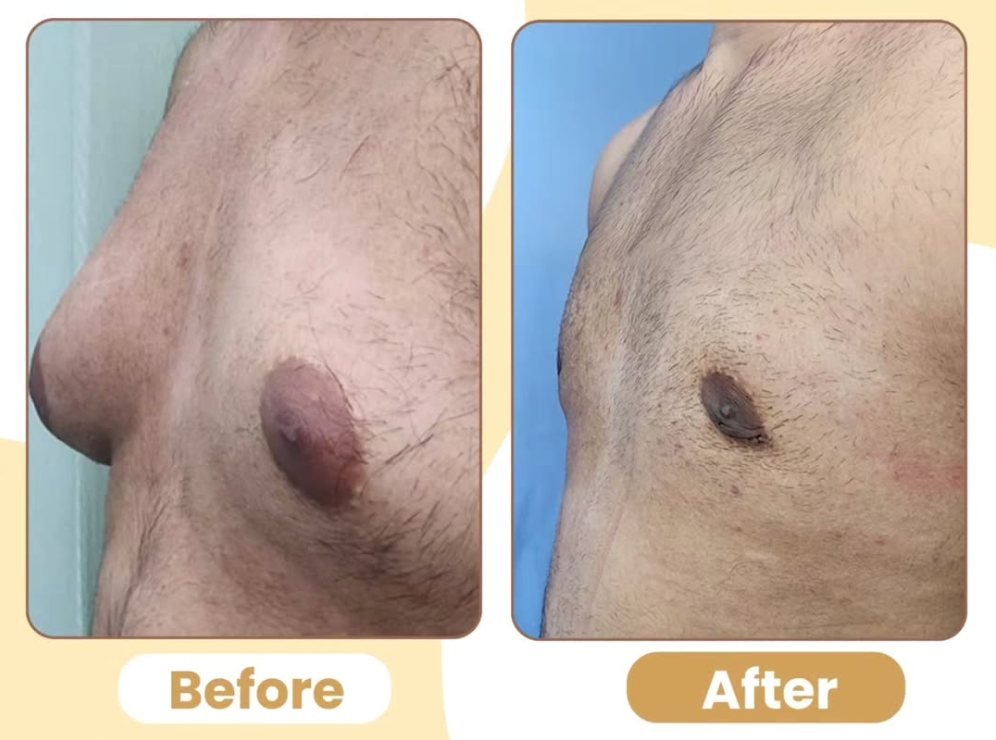
Most gynecomastia is benign. But certain features need proper assessment rather than a wait-and-see approach, because breast cancer in men — while rare, accounting for fewer than one in a hundred breast cancers — can present in a way that resembles gynecomastia.
See a doctor promptly if you notice:
To be clear about the relationship: gynecomastia does not turn into breast cancer. The reason these features matter is that cancer can look like gynecomastia, and needs to be ruled out.
Most men need no imaging at all. When clinical findings are clearly consistent with gynecomastia or pseudogynecomastia, further imaging is generally not required. Where there is any suspicion, ultrasound or mammography is used, along with blood tests to check hormone levels and liver, kidney and thyroid function.
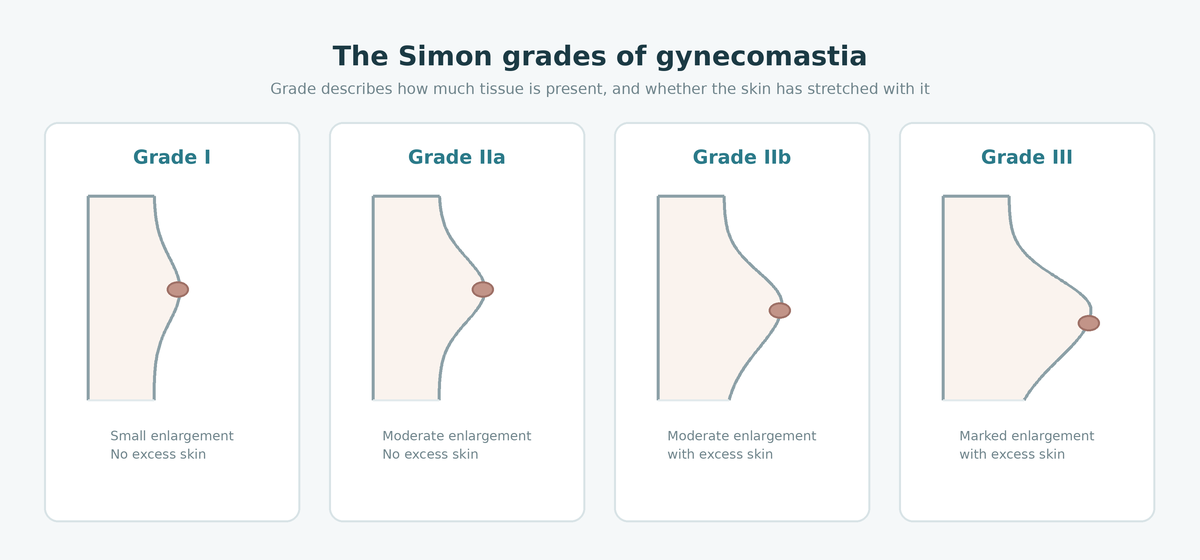
Surgeons commonly use the Simon classification. The grade largely determines the surgical approach:
| Grade | What it describes | Treatment usually required |
|---|---|---|
| I | Small breast enlargement, no excess skin | Liposuction with gland removal |
| IIa | Moderate enlargement, no excess skin | Liposuction with gland removal |
| IIb | Moderate enlargement with excess skin | Liposuction and gland removal, with a nipple–areola complex (NAC) lift |
| III | Marked enlargement with excess skin, enough that the chest begins to sag | Liposuction and gland removal, with skin excision |
The pattern is easy to follow once you see it. Every grade needs the same two things done to the tissue itself — the fat suctioned out and the glandular disc removed. What changes as the grade rises is what has to happen to the skin.
At Grades I and IIa the skin is still tight enough to redrape over the flatter chest on its own. At Grade IIb there is enough skin excess that the nipple and areola sit lower than they should once the volume beneath them is gone, so the nipple–areola complex is repositioned during the same operation. At Grade III there is more loose skin than repositioning alone can manage, and a formal skin excision becomes part of the procedure — which also means a longer scar, and that trade-off should be discussed openly beforehand.
Newer skin-sparing techniques have made it possible to avoid or reduce skin excision in some cases that would classically have required it, so grade is a guide to the likely approach rather than a fixed rule.
This is also where the fat-versus-gland distinction stops being academic. Liposuction is the tool for fatty tissue. Glandular tissue has to be cut out. The two tissues genuinely behave differently, right down to which instrument removes them.
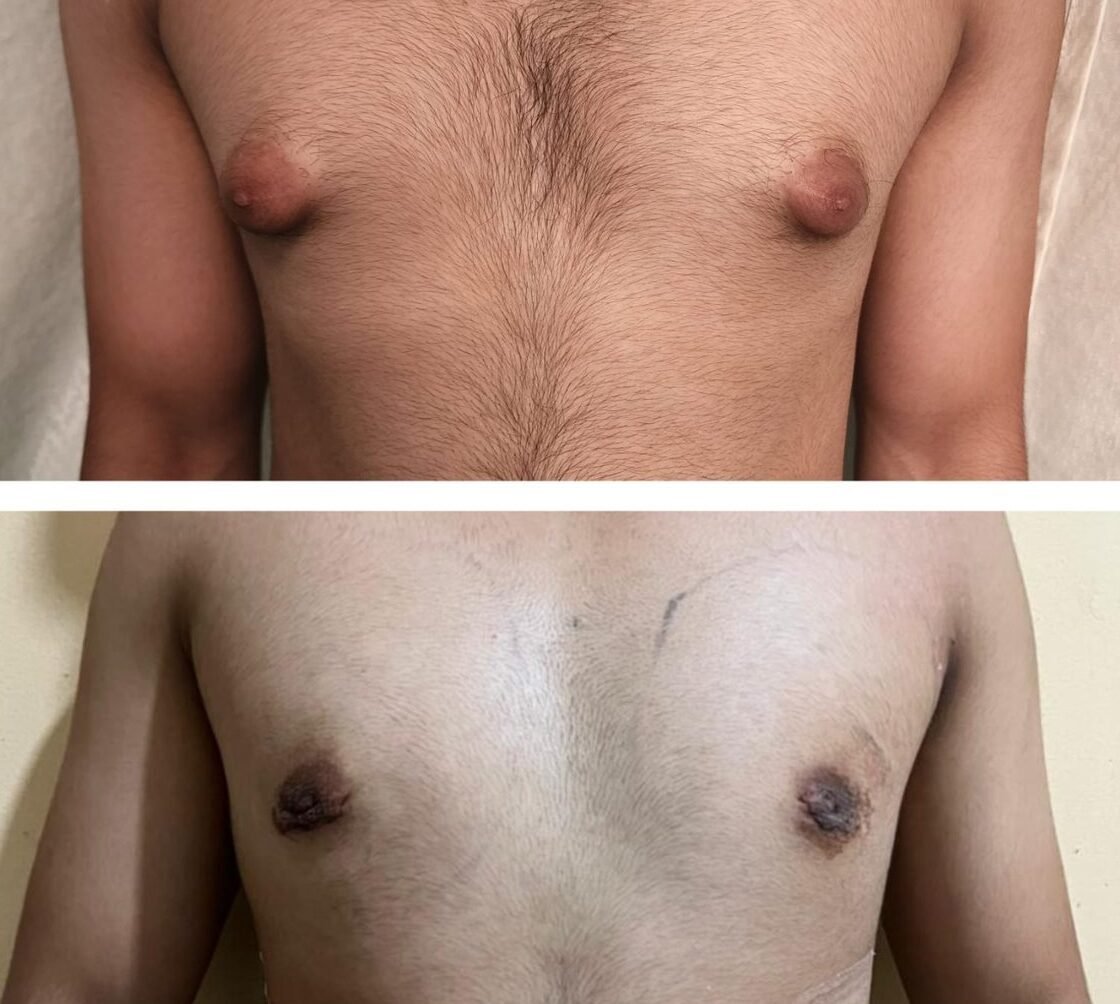
A lot of men wouldn’t describe their chest as enlarged at all. Their complaint is narrower: the nipple and areola look swollen, domed or cone-shaped, and it shows through a t-shirt.
That presentation usually has a straightforward explanation. A small glandular disc sitting immediately behind the areola pushes it forward, which makes the areola itself appear puffy and raised even when the chest overall looks normal. It tends to be most obvious in lean men, for the same reason described earlier — there is no surrounding fat to soften the outline.
In practice this is most often a Grade I presentation, and it is treated the same way: the glandular tissue behind the areola is removed, usually with liposuction to blend the surrounding contour so there is no visible step or dip. Because the volume removed is small and the skin is typically tight, additional skin work is rarely needed.
It is worth saying plainly that this is a real finding with a physical cause, not something to be talked out of. It behaves like glandular tissue because it is glandular tissue — which also means diet, training and time will not resolve it.
Sometimes, and the timing window is narrow.
Early gynecomastia is cellular, vascular and potentially reversible. Over months it becomes fibrous, and fibrous tissue does not regress. Published cut-offs for when that transition happens vary from around four months to twelve, but the direction is consistent: the earlier the intervention, the more likely it helps.
Tamoxifen has the best evidence of the drugs used, and even that evidence is weak. A systematic review of pharmacological treatment found only one randomised controlled trial across the entire literature; nearly everything else was case reports and small series. The authors concluded that tamoxifen is appropriate in selected patients but that high-quality publications are lacking. Aromatase inhibitors have performed poorly where properly tested — a randomised trial in 80 pubertal boys found anastrozole no more effective than placebo.
Two important caveats. These are prescription medicines with side effects, used outside their licensed indications, and they are not something to source or self-administer. And once gynecomastia is long-standing and fibrous, it is a surgical problem rather than a medical one — which is the situation most adult men searching this article are already in.
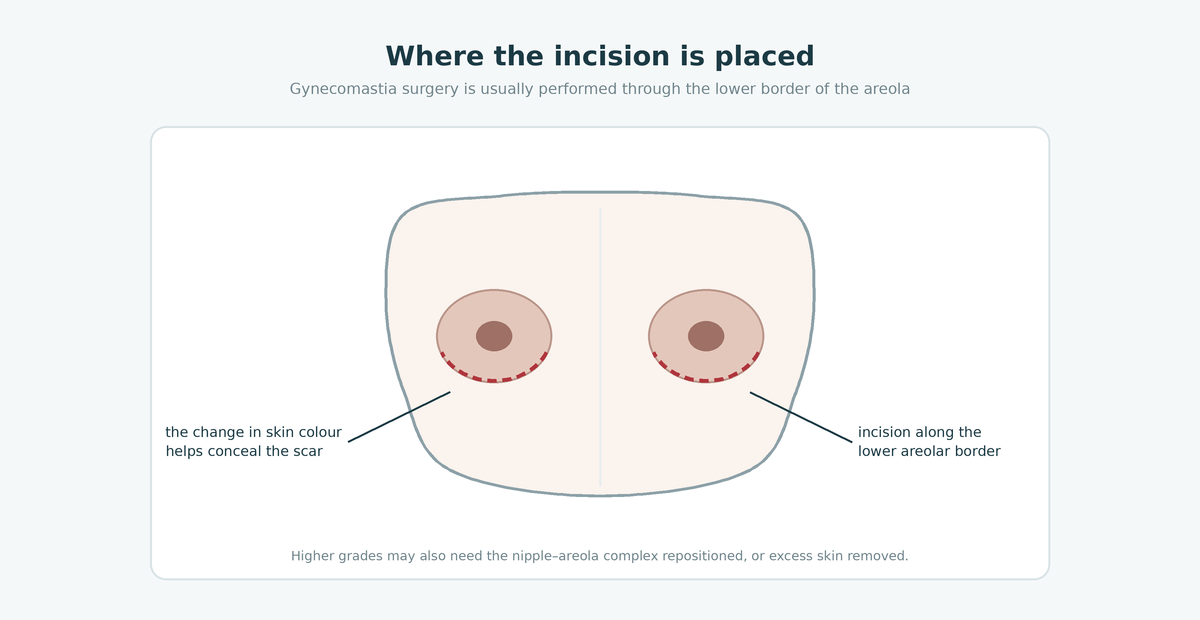
Surgery is generally considered when gynecomastia is long-standing, when medical treatment hasn’t worked or isn’t appropriate, when it interferes with daily life, or where there is diagnostic concern.
Gynecomastia surgery removes the glandular tissue directly — usually through a small incision at the lower border of the areola, where the change in skin colour helps conceal the healed scar. Liposuction is used alongside to address the fatty component and blend the contour into the surrounding chest. In higher grades, the nipple–areola complex is repositioned or skin is removed as described above.
Reported complication rates across skin-sparing techniques run in the range of 1.5–10%, with haematoma the most frequently reported at around 6%. Recognised risks include bleeding, fluid collection, infection, asymmetry, contour irregularity, changes in nipple sensation that can be temporary or permanent, poor wound healing, unfavourable scarring and the possibility of revision surgery. All breast reduction procedures leave scars.
Recovery is usually straightforward — soreness improving within about a week, back to work in around two weeks, with the final result apparent at roughly three to six months.
Results are generally lasting. Recurrence is uncommon, and the clearest documented risk factor is operating before puberty has finished. Beyond that, continuing the underlying cause — anabolic steroid use, an unchanged medication, an untreated hormonal condition, or substantial weight regain — can allow the problem to return. Addressing the driver matters as much as the operation.
There is a study worth knowing about, because it says something most men assume is not true of them.
Researchers compared 47 adolescents with gynecomastia against 92 healthy controls using validated instruments for quality of life and self-esteem. The gynecomastia group scored significantly lower on social functioning, mental health and self-esteem.
Two findings make it notable. First, the effect held independent of BMI — so this was not simply the effect of being overweight. Second, and more striking: severity made no difference to the scores. Men with mild gynecomastia were as affected as men with marked gynecomastia.
Which means the common response — “it’s barely noticeable, why does it bother you?” — is not just unhelpful. It is contradicted by the evidence. If a small amount of tissue is affecting how you dress, whether you swim, or how you feel in a changing room, that is a documented pattern, not an overreaction.
Work out which tissue you are dealing with. If the chest is soft and uniform and your weight is above where you’d like it, weight loss is the first and best intervention — for the fat, and for the hormonal picture.
If there is a firm, tender, disc-shaped area behind the nipple that hasn’t moved despite everything else changing, or if you are already lean and it is still there, that is glandular tissue, and no amount of training will remove it.
Either way, an examination takes minutes and settles the question properly — including whether a medication you are taking is the cause, which is more common than most men expect and is sometimes fixable without surgery at all.
In adolescents, usually yes — most cases resolve within six months to two years, and the majority within about three years. In adults, established glandular gynecomastia that has been present for more than a year rarely regresses, because the tissue has become fibrous by that point.
Exercise reduces chest fat, which helps if the problem is pseudogynecomastia. It does not remove glandular tissue. Chest exercises build the muscle beneath the gland, which in some men makes the gland more visible rather than less.
Because what you are left with is glandular tissue, not fat, and getting leaner does not remove it. In lean men it often becomes more obvious, since the surrounding fat that was softening the outline is gone and the pectoral muscle beneath pushes the gland forward.
Usually a small glandular disc sitting immediately behind the areola, pushing it forward so it looks domed or swollen. It is most noticeable in lean men and is typically a Grade I presentation, treated by removing the glandular tissue and blending the surrounding contour.
Lying flat, bring your thumb and forefinger together from either side of the nipple. Firm, rubbery, often tender tissue forming a disc around the nipple suggests gland. Soft, uniform tissue with no distinct edge suggests fat. An examination confirms it.
Yes — medication is the most common identifiable external cause. Spironolactone, finasteride, some antidepressants, certain antiretrovirals and several other drug classes are implicated. Anabolic steroids cause it through a different route: exogenous androgens are converted to oestradiol, which raises oestrogen activity at the breast.
Gynecomastia does not turn into breast cancer. Male breast cancer is rare — fewer than one in a hundred breast cancers occur in men — but it can look similar, which is why an off-centre, hard, fixed or one-sided lump, nipple discharge or skin changes should be assessed promptly.
Generally not. The clearest documented risk factor for recurrence is operating before puberty is complete, which is why surgery in teenagers is normally deferred. Continuing an underlying cause — steroids, a culprit medication, an untreated condition, significant weight regain — can also allow tissue to return.
The incision is usually placed at the border of the areola, where the change in colour helps conceal it. Higher grades that need skin removal have a longer scar, which should be discussed before surgery. Most settle to a fine line over 12 months, though healing varies between individuals.
Whether your chest is fat, gland, or both is a question an examination settles in minutes — and the answer determines everything else, including whether surgery is the right route at all.
Consultations with Dr. Priyanka Sharma in Ahmedabad are private, unhurried, and cover the parts most men want to ask about but don’t. If weight loss or a change in medication would solve it, you will be told that.
Read more about gynecomastia surgery and book a consultation





